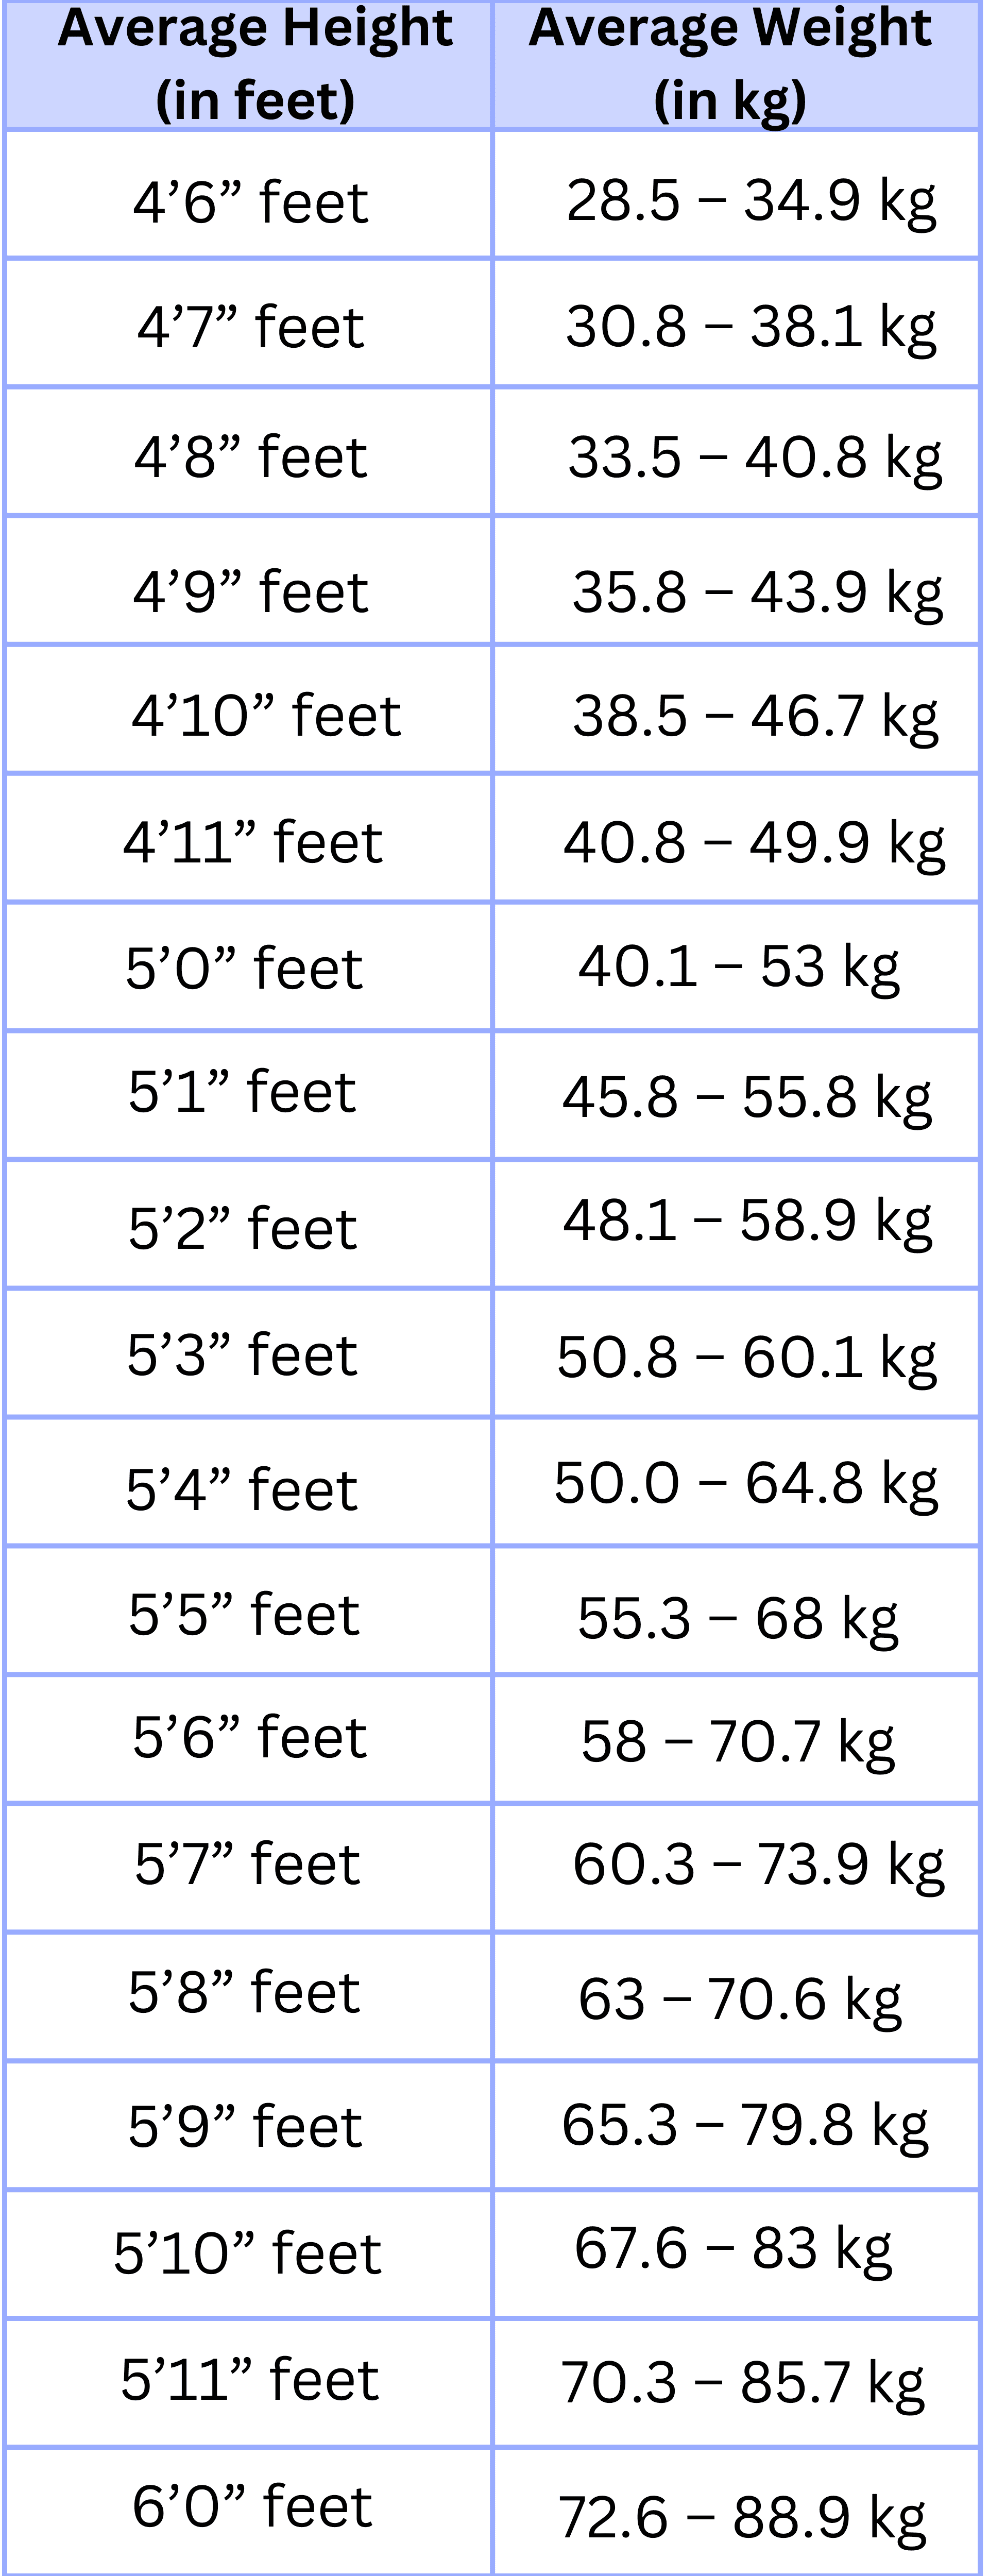
You’ve probably seen them. Those dusty, pixelated charts taped to the back of a doctor’s office door or buried in a 1990s health textbook. They claim that because you are a certain height and a certain age, you should weigh exactly 142 pounds. It’s a nice thought. Clean. Organized. But it’s mostly nonsense.
Bodies aren't math problems. They’re messy, biological engines that change gears every decade. If you are looking at height age and weight through the lens of a static spreadsheet, you are missing the actual story of your health. Honestly, the obsession with these three numbers in a vacuum has probably done more harm than good for most people's mental health.
Let's get real for a second. A 25-year-old athlete and a 65-year-old retiree might share the exact same height and weight. On paper, they look identical. In reality? One is carrying 15% body fat and high bone density, while the other might be struggling with sarcopenia—age-related muscle loss—and a metabolic rate that has slowed to a crawl. The numbers don't tell you who is "healthier." They just tell you how much force they exert on a scale.
The BMI Trap and Why We Can’t Quit It
The Body Mass Index (BMI) is the elephant in the room when we talk about height and weight. Developed in the 1830s by Adolphe Quetelet—a Belgian mathematician, not a doctor—it was never meant to diagnose individual health. Quetelet was trying to find the "average man" for social statistics. Yet, here we are, nearly 200 years later, still using a formula that ignores whether your weight comes from beer or bicep.
It’s flawed. We know this. But insurance companies and healthcare systems love it because it’s cheap and fast. It doesn't require a DEXA scan or a skinfold caliper. It just requires a tape measure and a scale.
The problem with relying on this for height age and weight correlations is that it fails the "LeBron James test." At his peak, LeBron was often classified as "overweight" or "obese" by standard BMI scales because of his massive muscle mass relative to his height. Muscle is dense. It’s heavy. If you’re active, your weight might stay high while your waistline shrinks. That is progress, even if the chart says you're failing.
How Age Actually Flips the Script
As we get older, the relationship between how tall we are and how much we weigh shifts in ways that standard charts rarely account for. It’s not just about "getting fat." It’s about "shifting."
Around age 30, most people start losing lean muscle mass—about 3% to 8% per decade. This is a huge deal. Muscle is metabolically active; it burns calories even when you’re just sitting there watching Netflix. When that muscle disappears and is replaced by fat, your weight might stay exactly the same. Your clothes might even fit the same. But your metabolic health is fundamentally different.
Then there’s the height factor. You actually do get shorter. The discs in your spine compress. Osteoporosis can cause the vertebrae to collapse slightly. By the time you’re 70, you might have lost an inch or two. If you’re trying to maintain the "ideal weight" for the height you had at 22, you’re chasing a ghost.
Interestingly, there is something called the "Obesity Paradox" in geriatric health. Research, including studies published in the Journal of the American Geriatrics Society, suggests that for people over age 65, being slightly "overweight" by BMI standards might actually be protective. It provides a reserve of energy if you get sick and offers a bit of padding if you fall. Being "thin" in old age is often a higher mortality risk than being a little bit heavy.
The Metabolism Myth
We used to think metabolism just fell off a cliff the moment you turned 30. We were wrong. A massive 2021 study published in Science, which looked at 6,600 people across 29 countries, found that metabolic rates remain remarkably stable from age 20 to age 60.
The "middle-age spread" isn't usually a broken metabolism. It’s a lifestyle shift. We move less. We sit in cars. We sit at desks. We have kids and stop going to the gym. The weight gain we associate with height age and weight changes in our 40s is often just the cumulative result of a thousand tiny choices rather than a biological betrayal.
Why "Ideal" is a Moving Target
If you look at the Metropolitan Life Insurance Company tables from the 1940s—the gold standard for decades—they were based on "actuarial data." Basically, they wanted to know which weight made you least likely to die and cost them money.
But "not dying" isn't the same as "thriving."
Your ideal weight is a range, not a point. It’s influenced by:
- Frame Size: Some people genuinely have "big bones." A wide pelvic structure and broad shoulders carry more mass than a narrow frame.
- Ethnicity: Research shows that the health risks associated with weight vary by ethnic background. For example, people of South Asian descent may face higher risks for type 2 diabetes at lower BMIs than people of European descent.
- Hydration and Hormones: You can swing 5 pounds in a single day just based on salt intake and water retention. For women, menstrual cycles can cause significant weight fluctuations that have zero to do with body fat.
Beyond the Scale: What to Track Instead
If the height and weight charts are broken, what are you supposed to use? You need better metrics.
Waist-to-Hip Ratio (WHR) is a big one. It measures where you carry your fat. Fat stored around the midsection (visceral fat) is inflammatory and dangerous for your heart. Fat stored on the hips and thighs (subcutaneous fat) is mostly just energy storage and far less risky. If your waist is more than half your height, that’s a much better indicator of health risk than the number on the scale.
Relative Fat Mass (RFM) is another emerging favorite. It’s a simple formula:
- Men: $64 - (20 \times (\text{height} / \text{waist circumference}))$
- Women: $76 - (20 \times (\text{height} / \text{waist circumference}))$
It tends to track much closer to actual body fat percentages measured by expensive medical equipment.
The Muscle Factor
You have to lift things. Seriously.
When we talk about height age and weight, the missing variable is almost always strength. In clinical settings, grip strength is often a better predictor of longevity than BMI. Why? Because it’s a proxy for total body muscle mass and neurological health.
If you’re 50 years old and your weight is creeping up, don't just starve yourself. If you go on a crash diet, you’ll lose fat, but you’ll also lose muscle. That makes your metabolism even slower, setting you up for a rebound where you gain even more fat back later. It's a vicious cycle. Instead, focus on protein intake and resistance training. You might stay "heavy" on the chart, but your body composition will shift toward health.
Real-World Examples of the Mismatch
Think about two people:
- Person A: 5'10", 200 lbs, 45 years old. Plays pickup basketball twice a week, lifts weights, eats a balanced diet. BMI says they are "Obese."
- Person B: 5'10", 160 lbs, 45 years old. Sedentary, smokes, eats mostly processed food, has very little muscle (skinny-fat). BMI says they are "Ideal."
Person B is statistically at a much higher risk for metabolic disease, heart issues, and early death. Yet, in a standard medical screening based on height age and weight, Person A is the one who gets the lecture about losing weight. This is the nuance that "expert" content often ignores.
Actionable Steps for Your "Actual" Health
Stop chasing a number from 1985. It’s time to modernize how you look at your body.
Get a baseline that matters.
Forget the scale for a month. Get a soft measuring tape and measure your waist at the belly button. Do this once every two weeks. If that number is going down or staying steady while your strength in the gym goes up, you’re winning.
Prioritize protein as you age.
To fight the muscle loss that messes up the height age and weight balance, you need more protein than you think. Aim for roughly 0.7 to 1 gram of protein per pound of your target body weight. This provides the building blocks to maintain the muscle you have.
Focus on "Power" not just "Weight."
Can you get up off the floor without using your hands? Can you carry your own groceries? Can you walk three miles without getting winded? these functional markers are the "real" charts you should be following.
Check your bloodwork.
If you’re worried about your weight, look at your A1C (blood sugar), your triglycerides, and your HDL/LDL cholesterol ratios. If these numbers are in the green, your "extra" 10 pounds of weight might not be the emergency the internet makes it out to be.
Adjust for the decade.
In your 20s, you can get away with a lot. In your 40s, you have to earn your health. In your 60s and 70s, your goal should be "durability." Don't compare your 50-year-old body to your 20-year-old self. It’s a different machine now. Treat it accordingly.
Health is a long game. The charts are just a snapshot of a moment in time, often based on outdated science. Listen to your body, move it often, and stop letting a metal box on the bathroom floor tell you what you're worth.



